Abstract: Peri-implantitis is a biofilm-associated inflammatory disease that results in progressive loss of the supporting tissues around dental implants and remains one of the greatest challenges in implant therapy. Successful treatment extends beyond implant surface decontamination and often requires adjunctive therapies to control infection, reduce inflammation, and facilitate regeneration of the lost peri-implant tissues. This second part of this review of peri-implantitis summarizes the current evidence regarding local and systemic antibiotic therapy, laser-assisted treatment, implantoplasty, and regenerative surgical approaches. Local antimicrobial agents may provide modest short-term clinical improvements when used as adjuncts to mechanical debridement, whereas routine systemic antibiotic therapy remains controversial because of limited long-term benefit and concerns regarding antimicrobial stewardship. Laser therapy may enhance implant surface decontamination and soft-tissue healing but has not consistently demonstrated superior long-term clinical outcomes. Implantoplasty may improve surface cleansability and reduce plaque retention but should be used judiciously because of potential titanium particle release and alteration of implant surface characteristics. Regenerative procedures can achieve predictable clinical and radiographic improvements in appropriately selected defects when combined with meticulous implant surface detoxification and effective plaque control, although true re-osseointegration remains difficult to confirm clinically. Overall, no single adjunctive modality has demonstrated consistent superiority, and successful peri-implantitis management requires a comprehensive, patient-specific treatment strategy that integrates biologic principles, surgical therapy, and long-term maintenance.
Peri-implantitis represents a complex biologic challenge that extends beyond the traditional microbial profile of periodontitis. Peri-implant lesions harbor a more diverse and heterogeneous microbiota, including opportunistic bacterial species and viral pathogens such as human cytomegalovirus and Epstein–Barr virus, which may contribute to disease progression through immunomodulatory mechanisms.1,2 These findings underscore that effective peri-implantitis management requires comprehensive disruption and modification of the peri-implant biofilm rather than simple bacterial reduction alone.
Although mechanical debridement remains the cornerstone of nonsurgical peri-implantitis therapy, its effectiveness is limited by implant surface roughness, thread geometry, and restricted access to contaminated implant surfaces within deep peri-implant defects.3 Consequently, mechanical therapy alone often fails to achieve predictable and sustained reductions in the peri-implant microbial burden sufficient to maintain long-term peri-implant tissue stability.3,4 This has led to the widespread investigation of adjunctive antimicrobial strategies to enhance treatment outcomes.
Antibiotic therapy has been incorporated into peri-implantitis management for more than three decades; however, its role—particularly the indications for local versus systemic delivery—remains controversial. Current evidence suggests that adjunctive antimicrobial therapy may provide modest short-term improvements in clinical parameters, particularly with locally delivered antibiotics, whereas long-term benefits remain uncertain and routine systemic antibiotic administration is not supported because of limited evidence and concerns regarding antimicrobial stewardship.
This article reviews the biologic rationale and clinical evidence supporting antibiotic therapy as an adjunct in peri-implantitis management and briefly situates antimicrobial use within a broader, evidence-based treatment framework that may also include laser-assisted decontamination and regenerative approaches.
Antibiotic Therapy
The microbial profile associated with peri-implantitis differs substantially from that of periodontitis. In addition to traditional anaerobic periodontal pathogens, peri-implant lesions harbor a broader and more heterogeneous microbial community that differs from that associated with periodontitis and includes opportunistic bacterial species and organisms not typically associated with periodontal disease and which may contribute to disease progression.1,2,5 These findings suggest that disruption and modification of the peri-implant biofilm may play a more critical role in disease management than simple bacterial reduction alone.
Given this complex microbial environment, antiseptic and antibiotic agents have been proposed as adjunctive modalities to enhance the outcomes of nonsurgical mechanical debridement. Mechanical therapy alone frequently fails to achieve bacterial reduction to levels compatible with long-term peri-implant tissue stability, particularly in advanced lesions characterized by deep peri-implant pockets, rough implant surface topography, and limited access for instrumentation.4,6,7
The adjunctive use of antimicrobial therapy in peri-implant disease was first introduced in 1992, when Mombelli and Lang demonstrated that reduction of subgingival bacterial load and suppression of anaerobic species following mechanical debridement resulted in improved clinical outcomes in peri-implantitis treatment.8,9 Despite these early findings, the role of antibiotic therapy, particularly regarding local versus systemic delivery, has remained controversial.
Most contemporary studies evaluate antimicrobial agents in combination with mechanical debridement rather than stand-alone therapies. Local delivery systems, including minocycline and doxycycline, have demonstrated moderate clinical benefits when used as adjuncts to mechanical debridement and antiseptic irrigation, particularly in moderately deep peri-implant defects.10-12 However, the additional clinical effects observed with local antibiotic delivery have generally been limited, in part due to inclusion of patients with advanced bone loss and complex defect morphologies. Importantly, available evidence provides little justification for the routine use of systemic antibiotics in nonsurgical peri-implantitis management.9
Nonsurgical debridement alone has consistently demonstrated limited long-term effectiveness in the treatment of peri-implantitis. While antiseptic agents such as chlorhexidine have been shown to improve clinical parameters, these benefits are typically transient and often diminish within 6 months.13 Adjunctive local antibiotics, including minocycline and doxycycline hyclate, have been associated with improvements in gingival inflammation and probing depth reduction; further long-term randomized studies, however, are required to confirm sustained clinical efficacy.14
Systematic reviews reported modest improvements in probing depth, averaging approximately 0.3 mm, and reductions in bleeding on probing (BOP) following topical antibiotic application, with no reported adverse effects.15 Notably, no statistically significant differences were identified between minocycline and chlorhexidine therapies. Similarly, other reports have demonstrated improved probing depth and bleeding indices in peri-implantitis cases treated with local antibiotics in conjunction with nonsurgical therapy compared with nonsurgical therapy alone.16
A meta-analysis revealed statistically significant reductions in probing depth, radiographic bone level gains, and higher overall treatment success rates when antibiotics were used as adjunctive therapy for peri-implant disease.17 In contrast, another study reported that adjunctive systemic antibiotics provided significant clinical benefits at 1 year when used alongside both nonsurgical and surgical peri-implantitis therapies.18 Despite these findings, systemically delivered antibiotics are invariably administered in conjunction with additional therapeutic interventions, complicating interpretation of their independent efficacy. Consequently, there remains no clear indication for routine systemic antibiotic use in peri-implantitis management, and such prescriptions should be discouraged due to questionable long-term benefit and concerns regarding antimicrobial resistance.17,19
Local Vs Systemic Antibiotics
Antibiotics used as adjuncts in peri-implantitis management include minocycline, doxycycline, lincomycin, erythromycin, tetracycline, amoxicillin, azithromycin, and metronidazole. Depending on the antimicrobial agent and treatment approach, local delivery formulations may include gels, microspheres, fibers, powders, and ointments; certain antibiotics also have been incorporated into graft materials.
Nonsurgical debridement alone is ineffective for long-term treatment of peri-implantitis. Antiseptic agents such as chlorhexidine improve clinical outcomes but only for up to 6 months. Concomitant antibiotics such as minocycline and doxycycline have improved gingival inflammation and probing depths. Further studies are needed to verify long-term efficacy.20
Improvement in periodontal probing depth (PPD) (average 0.3mm) and BOP after topical administration of antibiotics, without adverse effects, was reported.15 Minocycline application and chlorhexidine were not significantly different. An improvement in PPD and BOP has been reported in cases of peri-implantitis treated with local antibiotics and nonsurgical treatment compared with nonsurgical treatment alone.21 A significant reduction in probing depth, a gain in radiographic bone level, and greater treatment success rate have been reported when using antibiotics as adjunctive treatment for peri-implant disease.17 Nonsurgical treatment of peri-implantitis with adjunctive systemic antibiotics was found to lead to significant benefits in probing depth reduction, clinical attachment level gain, and suppuration reduction at 1 year.18 Surgical treatment with adjunctive systemic antibiotics showed significant benefits in terms of bone gain and clinical success at 1 year.
Systemically delivered antibiotics are always given in combination with other interventions. Some studies demonstrate improvement in PPD and BOP when amoxicillin and metronidazole are given in combination with nonsurgical treatments. Other studies showed no improvement in PPD or BOP but did show improvement in secondary outcomes such as reduced clinical attachment level, less suppuration, recession, and bone loss, and lower total bacteria count.22 The use of systemic antibiotics with peri-implantitis treatment remains controversial, with no clear indication for the use of systemically delivered antibiotics for treating peri-implantitis.17 Prescription of systemic antibiotics for peri-implantitis should be discouraged due to the questionable efficacy and contribution toward antimicrobial resistance.
Laser Therapy as an Adjunctive Modality in Peri-Implantitis Management
Laser therapy was introduced into periodontal and peri-implant treatment protocols in the 1990s as an adjunct to conventional mechanical debridement; the goal was to enhance implant surface decontamination while minimizing damage to surrounding hard and soft tissues. Since its introduction, multiple laser wavelengths and delivery systems have been evaluated for their ability to disrupt microbial biofilms, reduce peri-implant inflammation, and support soft-tissue healing around affected implants. An American Academy of Periodontology best evidence review concluded that laser therapy represents a viable adjunctive approach for the management of peri-implant mucositis and peri-implantitis, particularly when used in conjunction with conventional therapy rather than as a replacement for it.23
Among currently available systems, erbium-based lasers, specifically Er:YAG and Er,Cr:YSGG, have received the most attention in peri-implant therapy due to their high affinity for water and hydroxyapatite. These lasers allow effective removal of bacterial biofilm and surface contaminants from exposed implant threads while producing minimal thermal damage to the surrounding bone when appropriate power settings and cooling protocols are used.23 The ability to decontaminate complex implant surface topography without direct mechanical contact is particularly advantageous in peri-implantitis cases, where excessive heat generation or surface alteration may compromise osseointegration.
In addition to surface decontamination, erbium lasers have demonstrated favorable biologic effects on soft-tissue healing. Experimental evidence suggests that Er:YAG laser irradiation promotes gingival wound repair through photodissociation of water molecules, leading to enhanced cellular activity and improved early healing responses.24 Antimicrobial photodynamic therapy (aPDT) has also been investigated as an adjunctive approach for peri-implantitis management. Unlike erbium lasers, aPDT combines a photosensitizing agent with low-energy laser light to generate reactive oxygen species that selectively destroy microbial cells while minimizing damage to host tissues. Systematic reviews have demonstrated modest short-term reductions in BOP and peri-implant inflammation; however, current evidence does not support superior long-term clinical outcomes compared with conventional mechanical debridement alone.7,25 These biologic effects may contribute to the consistent short-term reductions in BOP and peri-implant inflammation observed in clinical studies following laser-assisted therapy.
From a clinical perspective, laser therapy offers several practical advantages when incorporated as an adjunctive modality. Laser energy can access irregular implant surfaces, thread undercuts, and micro-roughened areas that are often difficult to debride thoroughly using curettes or ultrasonic instrumentation alone.26 Furthermore, laser therapy is minimally invasive and generally well tolerated by patients and may be associated with reduced postoperative discomfort and early soft-tissue inflammation compared with conventional therapy.27 Importantly, erbium laser irradiation has been shown not to adversely affect mineralized tissues when used within recommended parameters, supporting its safety profile in peri-implant applications.28
Despite these advantages, the current body of evidence indicates that clinical outcomes achieved with laser therapy are largely comparable to those obtained with conventional mechanical debridement alone. Systematic reviews and meta-analyses have demonstrated that while laser-assisted surface detoxification may lead to short-term improvements, particularly reductions in BOP, there is limited evidence of superior long-term gains in probing depth reduction or radiographic bone regeneration when compared with conventional approaches.7,29
Nonetheless, nonsurgical laser therapy may play a valuable adjunctive role in early or moderate peri-implantitis cases, especially in situations where surgical intervention is contraindicated or delayed. A recent systematic review and meta-analysis evaluating nonsurgical laser therapy reported modest reductions in inflammation and probing depths; however, significant heterogeneity in study design, laser parameters, and treatment protocols limited definitive conclusions regarding long-term efficacy.27 These findings underscore the need for standardized clinical protocols and longer-term controlled studies to more clearly define the indications and limitations of laser therapy in peri-implantitis management.
In contemporary peri-implant practice, laser therapy may be viewed as a complementary component within a comprehensive treatment strategy that includes meticulous mechanical debridement, appropriate chemical surface detoxification, and management of patient-specific risk factors. When used judiciously and within evidence-based parameters, lasers may enhance soft-tissue healing, improve patient comfort, and support short-term clinical improvements while reinforcing a minimally invasive, biologically driven approach to peri-implant disease management.
Clinical Application of Laser Therapy in Peri-Implantitis Treatment
When used in the treatment of peri-implantitis, laser therapy is typically performed as an adjunct to thorough mechanical debridement and begins with removal of supra- and submucosal biofilm and calculus using conventional instrumentation. Following initial debridement, the laser fiber or tip is introduced into the peri-implant pocket and directed along the exposed implant surface and inflamed soft tissues, with care taken to maintain appropriate angulation and movement to ensure uniform energy distribution. Erbium-based lasers are commonly operated at low to moderate energy settings with copious water irrigation to minimize thermal effects while facilitating disruption of bacterial biofilm and detoxification of the implant surface. The laser is applied circumferentially around the implant to access thread undercuts and micro-roughened surfaces that may be difficult to reach mechanically. Treatment endpoints include visible reduction of bleeding, improved tissue tone, and decontamination of exposed implant threads.
Laser therapy may be performed as part of a nonsurgical protocol or incorporated intraoperatively during surgical access procedures to enhance surface decontamination prior to regenerative or resective therapy. Careful adherence to manufacturer-recommended parameters and evidence-based protocols is essential to maximize efficacy while preserving implant surface integrity and surrounding bone.
Regenerative and laser-assisted therapy for peri-implantitis involves a structured, stepwise approach focused on disruption of the biofilm, detoxification of the implant surface, and resolution of peri-implant inflammation. The initial presentation demonstrates inflamed peri-implant soft tissues with BOP, increased probing depths, and crestal bone loss, with biofilm and calculus evident along the exposed implant threads (Figure 1 A). Mechanical debridement utilizing implant-safe instruments is performed to remove bulk deposits and disrupt the biofilm, thereby exposing the contaminated implant surface for further treatment (Figure 1 B). A laser fiber is introduced into the peri-implant pocket and positioned parallel to the implant surface, allowing controlled circumferential delivery of laser energy to the affected area (Figure 1 C).
Laser-mediated bacterial reduction and surface decontamination then occurs, where laser energy facilitates disruption of residual biofilm and reduction of the microbial load through photothermal and/or photomechanical effects (Figure 1 D). Laser curettage with ablation of the diseased pocket epithelium and granulation tissue is then performed, contributing to reduction of inflammation and promotion of a healthier connective tissue interface (Figure 1 E). The post-treatment condition is, ideally, reduced inflammation, improved soft-tissue adaptation, and stabilization of peri-implant tissues (Figure 1 F).
Collectively, this sequence highlights the role of laser therapy as an adjunct to mechanical debridement in the management of peri-implantitis. It is aimed at enhancing decontamination and improving clinical outcomes, although true re-osseointegration remains unpredictable.
When peri-implantitis has resulted in minor crestal bone loss with limited implant thread exposure, osseous resective therapy with or without implantoplasty may be indicated to facilitate improved long-term maintenance. Osseous resective therapy is most appropriate for peri-implantitis defects characterized by predominantly horizontal bone loss, supracrestal implant thread exposure, or non-contained defects where predictable regenerative therapy is unlikely to achieve re-osseointegration. The primary objective is to eliminate peri-implant pockets, establish a maintainable soft-tissue architecture, and facilitate long-term plaque control rather than regenerate lost supporting bone.30-32 By converting a rough, plaque-retentive surface into a smoother, more cleansable profile through implantoplasty, this approach improves the patient’s ability to perform effective homecare, thereby enabling reduced biofilm accumulation and decreasing the risk of recurrent peri-implant inflammation and disease progression.
This scenario is depicted in Figure 2. Treatment is initiated with removal of the prosthesis to allow direct access to the affected implant surface (Figure 2 A), followed by mechanical debridement of biofilm and subgingival calculus deposits (Figure 2 B). Implantoplasty is then performed in which exposed implant threads are reduced and smoothed using rotary instrumentation to eliminate surface irregularities that promote plaque retention (Figure 2 C and D). Subsequent surface refinement is achieved with brushing to further polish the implant (Figure 2 E). Finally, adjunctive air-powder abrasion and chemical disinfection is done to enhance surface decontamination (Figure 2 F).
Regenerative Therapy for Peri-Implantitis
The reported success of regenerative therapy in peri-implantitis treatment varies widely across studies, reflecting differences in defect morphology, surgical protocols, biomaterials, and patient selection.33 Radiographic bone gain does not necessarily correlate with true re-osseointegration of the implant surface, as definitive confirmation requires histologic evaluation.34 Success of regenerative therapy varies from study to study.28 Definitive proof of re-osseointegration requires histologic evaluation of the treated implant and surrounding tissues, which is difficult to obtain in human patients.34 If the disease affects peri-implant bone, causing its resorption and resulting in progressive bone loss, the regenerative therapy is aimed at repairing and restoring the missing or lost peri-implant structures through re-osseointegration. Several critical factors influence regenerative success, including effective biofilm removal, implant surface quality, thorough decontamination, defect morphology, plaque control, and the adjunctive use of biologic modifiers.35
Peri-implant defect configuration has been identified as one of the most influential determinants of regenerative success.33 Froum reported outcomes from 170 consecutive implants treated using a protocol that incorporated growth factors and bone grafts, demonstrating high implant retention even in advanced peri-implantitis cases.34 Treatment utilized eight essential biomaterials, including platelet-derived growth factor (PDGF), mineralized freeze-dried bone allograft (MFDBA), and recombinant platelet-derived growth factor (rhPDGF). Of the implants treated, 48 had advanced peri-implantitis with more than 50% bone loss, and 47 out of these 48 had successful outcomes and were retained. This protocol consisted of: case selection, flap access, surface decontamination, defect debridement while dressing the implant surface with Emdogain® (Straumann, straumann.com) and/or PDGF, filling the defect using bone allograft and/or bovine xenograft, placement of an absorbable membrane or subepithelial connective tissue graft with coronal positioning of the flap, and professional maintenance/monitoring long-term (Table 1). Autologous blood concentrates and biologic agents have demonstrated additive effects on re-osseointegration. You et al identified histologic re-osseointegration in 50% of treated implants using autologous bone grafts with platelet-rich fibrin (PRF).36 Long-term studies further support regenerative therapy, with sustained clinical and radiographic improvements reported up to 10 years post-treatment.37
The most important factors affecting re-osseointegration are efficacy of biofilm removal, quality of the implant surface, decontamination and conditioning, successful defect site correction for adequate oral hygiene maintenance, effective plaque control, and use of grafts with growth factors for tissue regeneration.35 Additionally, peri-implant defect configuration is a critical factor related to success of peri-implantitis regenerative procedures, making careful selection of defect morphology highly important.33 Several studies have demonstrated regenerated bone upon surgical re-entry of the site and comparison with initial bone levels.38
Use of growth factors and autologous blood concentrates have been investigated for their potential additive effect on re-osseointegration. One study identified re-osseointegration in 50% of diseased implants treated with autologous bone graft with PRF without membranes.36 Another study found higher re-osseointegration after incorporating autologous periodontal ligament stem cells (PDLSCs) and bone morphogenetic protein (BMP)-2-expressing autologous PDLSCs.39 This was supported by a study that showed that a combination of beta-tricalcium phosphate and endothelial progenitor cells enhanced bone formation following surgical therapy.40 A systematic review found radiographic bone level fill was 2 mm, probing depth reduction was 2.78 mm, and BOP was reduced by more than 50%41; there was a high variation in defect morphology, surgical protocols, and selection of biomaterials, but results showed an improvement of clinical scenarios after surgical regenerative approach to peri-implantitis.
Interestingly, a barrier membrane or submerged healing did not seem mandatory for a successful outcome. These results are supported by a study that found significant improvements in BOP and probing depth values compared with non-augmentative surgical therapies.42 A study acknowledged that surgical regenerative peri-implantitis therapy improved clinical and radiographic treatment outcomes compared with baseline, with up to 10 years’ follow-up.37 These reported finding were supported in a study that achieved a greater mean reduction in probing depth (3.1 mm) when using bovine-derived xenograft and collagen membrane, compared with the lowest reduction (1.2 mm), which was observed in patients treated with implantoplasty and saline rinse.43
Regenerative therapy for peri-implantitis involves a structured, stepwise approach aimed at eliminating infection, detoxifying the implant surface, and reconstructing the lost peri-implant supporting bone (Figure 3). Baseline findings demonstrate peri-implant inflammation characterized by increased probing depths, BOP, biofilm accumulation, and associated crestal bone loss with exposure of implant threads (Figure 3 A). Thorough mechanical debridement with removal of granulation tissue and implant surface decontamination, is done, which is critical to disrupt the biofilm and reduce the microbial load that perpetuates the inflammatory process (Figure 3 B). A particulate bone graft is placed into the peri-implant defect to re-establish the lost osseous volume and provide a scaffold for new bone formation, particularly in contained or circumferential defects (Figure 3 C). Placement of a resorbable membrane over the grafted site then facilitates guided bone regeneration by stabilizing the graft and excluding epithelial and connective tissue ingrowth that may compromise regeneration (Figure 3 D). Tension-free primary closure is achieved with suturing of the soft-tissue flap, ensuring wound stability, protection of the regenerative site, and maintenance of the graft–membrane complex during early healing (Figure 3 E). The anticipated clinical outcome following healing includes resolution of inflammation, reduction in probing depths, and radiographic evidence of improved bone fill surrounding the implant, all signs that are indicative of successful regenerative therapy and re-establishment of peri-implant health (Figure 3 F).
Discussion
Peri-implantitis is a biologically complex disease process that extends beyond a simple bacterial infection and reflects dynamic interactions between the peri-implant biofilm and the host immune response. The presence of opportunistic microorganisms and viral pathogens reinforces that successful management depends on effective disruption of the biofilm and modulation of the local inflammatory environment rather than attempts at complete microbial eradication.
Mechanical debridement remains the foundation of nonsurgical peri-implantitis therapy; its effectiveness, however, is limited by implant surface roughness, thread geometry, and restricted access within deeper peri-implant defects. As disease severity increases, these limitations reduce the predictability of biofilm disruption and implant surface decontamination, limiting the long-term success of nonsurgical therapy alone. Consequently, considerable research has focused on adjunctive treatment modalities designed to enhance implant surface decontamination, reduce microbial burden, and improve clinical outcomes when combined with conventional mechanical instrumentation.
Adjunctive antimicrobial strategies have therefore been investigated to improve the effectiveness of nonsurgical therapy. Locally delivered antibiotics may provide modest short-term benefits when combined with mechanical debridement and antiseptic measures, particularly in early or moderate disease where defects remain accessible and maintainable. In contrast, routine use of systemic antibiotics offers limited additional benefit, is confounded by concurrent therapies, and raises concerns related to antimicrobial stewardship. Accordingly, systemic antibiotics should not be considered a routine component of peri-implantitis management. The principal nonsurgical treatment modalities, including their indications, clinical steps, advantages, and limitations, are summarized in Table 2.
Laser-assisted therapy has emerged as an adjunctive treatment intended to overcome some of the mechanical limitations of conventional instrumentation. Erbium lasers, particularly Er and Er,Cr systems, can effectively decontaminate complex implant surface topography while minimizing thermal injury when used with appropriate power settings and cooling protocols. Antimicrobial photodynamic therapy has also demonstrated modest short-term improvements in inflammatory parameters, although neither modality has consistently demonstrated superior long-term clinical outcomes compared with conventional therapy alone.
As disease progression results in more advanced bone loss and exposed implant threads, surgical intervention frequently becomes necessary. Implantoplasty and osseous resective therapy improve access for plaque control by creating a smoother, more maintainable implant surface, making these treatments particularly useful in non-contained defects where regenerative therapy is unlikely to achieve predictable re-osseointegration. Conversely, regenerative procedures are indicated for contained infrabony defects with favorable morphology, where bone grafts, biologic mediators, barrier membranes, and soft-tissue augmentation may improve clinical attachment, radiographic bone fill, and peri-implant tissue stability.
Despite continued advances in implant surface decontamination, biologic enhancement, and regenerative techniques, no single therapeutic approach has demonstrated consistent superiority across all peri-implant defect configurations. Treatment selection should therefore be individualized according to defect morphology, implant position, prosthetic design, patient-related risk factors, and the ability to establish long-term plaque control through supportive peri-implant maintenance.
Conclusions
Mechanical debridement remains the foundation of peri-implantitis therapy but is insufficient as a predictable stand-alone treatment for established disease because of complex implant surface topography and limited access to contaminated implant threads. Adjunctive treatment modalities—including locally delivered antimicrobials, laser-assisted therapy, antimicrobial photodynamic therapy, implantoplasty, and regenerative surgical procedures—may enhance clinical outcomes when appropriately selected according to defect morphology, disease severity, and patient-specific risk factors.
Current evidence suggests that locally delivered antimicrobials and laser-based therapies provide modest improvements in short-term clinical parameters, whereas routine systemic antibiotic use is not supported because of limited long-term benefit and antimicrobial considerations. Implantoplasty and osseous resective therapy remain valuable options for non-contained defects with exposed implant threads, while regenerative procedures are best reserved for infrabony defects with favorable regenerative potential.
No single therapeutic approach has demonstrated consistent superiority across all clinical presentations. Successful management of peri-implantitis therefore requires an individualized, evidence-based treatment strategy that integrates meticulous implant surface decontamination, appropriate adjunctive therapies, defect-specific surgical management when indicated, and long-term supportive peri-implant maintenance to maximize implant survival.
ACKNOWLEDGMENT
Figure 1 through Figure 3 are artificial intelligence (AI)–generated illustrations (ChatGPT) created by the authors.
ABOUT THE AUTHORS
Kenneth Lee, BDS, MSc
Private Practice, Sydney, Australia
Kevin Ka Yiu Shum, BMedSc, DMD
Private Practice, Sydney, Australia
Gregori M. Kurtzman, DDS, MAGD
Former Assistant Clinical Professor, University of Maryland School of Dentistry, Baltimore, Maryland; Private Practice, Silver Spring, Maryland
References
1. Kotsakis GA, Olmedo DG. Peri-implantitis is not periodontitis: scientific discoveries shed light on microbiome-biomaterial interactions that may determine disease phenotype. Periodontol 2000. 2021;86(1):231-240.
2. Akram Z, Al-Aali KA, Alrabiah M, et al. Current weight of evidence of viruses associated with peri-implantitis and peri-implant health: a systematic review and meta-analysis. Rev Med Virol. 2019;29(3):e2042.
3. Cosgarea R, Roccuzzo A, Jepsen K, et al. Efficacy of mechanical/physical approaches for implant surface decontamination in non-surgical submarginal instrumentation of peri-implantitis. A systematic review. J Clin Periodontol. 2023;50(suppl 26):188-211.
4. Barbato L, Cavalcanti R, Rupe C, et al. Clinical efficacy of adjunctive methods for the non-surgical treatment of peri-implantitis: a systematic review and meta-analysis. BMC Oral Health. 2023;23(1):375.
5. Sahrmann P, Gilli F, Wiedemeier DB, et al. The microbiome of peri-implantitis: a systematic review and meta-analysis. Microorganisms. 2020;8(5):661.
6. Acar B, Guncu GN. Current status and management of peri-implantitis: a systematic review. Prim Dent J. 2024;13(4):77-92.
7. Ramanauskaite A, Schwarz F, Cafferata EA, Sahrmann P. Photo/mechanical and physical implant surface decontamination approaches in conjunction with surgical peri-implantitis treatment: a systematic review. J Clin Periodontol. 2023;50(suppl 26):317-335.
8. Mombelli A, Lang NP. Antimicrobial treatment of peri-implant infections. Clin Oral Implants Res. 1992;3(4):162-168.
9. Grusovin MG, Pispero A, Del Fabbro M. Antibiotics as adjunctive therapy in the non-surgical treatment of peri-implantitis: a systematic review and meta-analysis. Antibiotics (Basel). 2022;11(12):1766.
10. Renvert S, Lessem J, Dahlén G, et al. Topical minocycline microspheres versus topical chlorhexidine gel as an adjunct to mechanical debridement of incipient peri-implant infections: a randomized clinical trial. J Clin Periodontol. 2006;33(5):362-369.
11. Büchter A, Meyer U, Kruse-Lösler B, et al. Local antibiotic therapy in peri-implantitis. J Periodontol. 2004;75(5):752-758.
12. Muthukuru M, Zainvi A, Esplugues EO, Flemmig TF. Non-surgical therapy for the management of peri-implantitis: a systematic review. Clin Oral Implants Res. 2012;23 suppl 6:77-83.
13. Heitz-Mayfield LJ, Lang NP. Antimicrobial treatment of peri-implant diseases. Int J Oral Maxillofac Implants. 2004;19 suppl:128-139.
14. Salvi GE, Persson GR, Heitz-Mayfield LJ, et al. Adjunctive local antibiotic therapy in the treatment of peri-implantitis II: clinical and radiographic outcomes. Clin Oral Implants Res. 2007;18(3):281-285.
15. Toledano M, Osorio MT, Vallecillo-Rivas M, et al. Efficacy of local antibiotic therapy in the treatment of peri-implantitis: a systematic review and meta-analysis. J Dent. 2021;113:103790.
16. Javed F, Alghamdi AS, Ahmed A, et al. Clinical efficacy of antibiotics in the treatment of peri-implantitis. Int Dent J. 2013;63(4):169-176.
17. Wang Y, Chen CY, Stathopoulou PG, et al. Efficacy of antibiotics used as an adjunct in the treatment of peri-implant mucositis and peri-implantitis: a systematic review and meta-analysis. Int J Oral Maxillofac Implants. 2022;37(2):235-249.
18. Okuma-Oliveira B, Dos Reis INR, Souto MLS, et al. The adjunctive use of systemic antibiotics in the non-surgical and surgical treatment of peri-implantitis: a systematic review and meta-analysis. Int J Oral Implantol (Berl). 2024;17(4):359-380.
19. Teoh L, Löffler C, Mun M, et al. A systematic review of dental antibiotic stewardship interventions. Community Dent Oral Epidemiol. 2025;53(3):245-255.
20. Mombelli A, Müller N, Cionca N. The epidemiology of peri-implantitis. Clin Oral Implants Res. 2012;23 suppl 6:67-76.
21. Passarelli PC, Netti A, Lopez MA, et al. Local/topical antibiotics for peri-implantitis treatment: a systematic review. Antibiotics (Basel). 2021;10(11):1298.
22. Toledano-Osorio M, Vallecillo C, Toledano R, et al. A systematic review and meta-analysis of systemic antibiotic therapy in the treatment of peri-implantitis. Int J Environ Res Public Health. 2022;19(11):6502.
23. Lin GH, Suárez López Del Amo F, Wang HL. Laser therapy for treatment of peri-implant mucositis and peri-implantitis: an American Academy of Periodontology best evidence review. J Periodontol. 2018;89(7):766-782.
24. Lubart R, Kesler G, Lavie R, Friedmann H. Er:YAG laser promotes gingival wound repair by photo-dissociating water molecules. Photomed Laser Surg. 2005;23(4):369-372.
25. Albaker AM, ArRejaie AS, Alrabiah M, et al. Effect of antimicrobial photodynamic therapy as an adjunct to mechanical debridement in the treatment of peri-implant diseases: a systematic review and meta-analysis. Photodiagnosis Photodyn Ther. 2018;21:147-152.
26. Ravidà A, Saleh MHA, Wang IC, et al. Efficacy of decontamination methods for biofilm removal from dental implant surfaces and reosseointegration: a systematic review. Int J Oral Maxillofac Implants. 2025;40(3):497-516.
27. Srinivasan M, Kamnoedboon P, Papi P, Romeo U. Efficacy of non-surgical laser therapy for the management of peri-implantitis: a systematic review and meta-analysis. J Dent. 2025;154:105562.
28. Mollabashi V, Rezaei-Soufi L, Farhadian M, Noorani AR. Effect of erbium, chromium-doped: yttrium, scandium, gallium, and garnet and erbium: yttrium-aluminum-garnet laser etching on enamel demineralization and shear bond strength of orthodontic brackets. Contemp Clin Dent. 2019;10(2):263-268.
29. Mailoa J, Lin GH, Chan HL, et al. Clinical outcomes of using lasers for peri-implantitis surface detoxification: a systematic review and meta-analysis. J Periodontol. 2014;85(9):1194-1202.
30. Monje A, Schwarz F. Principles of combined surgical therapy for the management of peri-implantitis. Clin Adv Periodontics. 2022;12(1):57-63.
31. Romeo E, Ghisolfi M, Murgolo N, et al. Therapy of peri-implantitis with resective surgery. A 3-year clinical trial on rough screw-shaped oral implants. Part I: clinical outcome. Clin Oral Implants Res. 2005;16(1):9-18.
32. Matarasso S, Iorio Siciliano V, Aglietta M, et al. Clinical and radiographic outcomes of a combined resective and regenerative approach in the treatment of peri-implantitis: a prospective case series. Clin Oral Implants Res. 2014;25(7):761-767.
33. Mordini L, Sun N, Chang N, et al. Peri-implantitis regenerative therapy: a review. Biology (Basel). 2021;10(8):773.
34. Froum SJ. Treatment of advanced peri-implantitis with regenerative therapy: a review of the rationale, technique and outcomes. Front Oral Maxillofac Med. 2022;4:37.
35. Subramani K, Wismeijer D. Decontamination of titanium implant surface and re-osseointegration to treat peri-implantitis: a literature review. Int J Oral Maxillofac Implants. 2012;27(5):1043-1054.
36. You TM, Choi BH, Zhu SJ, et al. Treatment of experimental peri-implantitis using autogenous bone grafts and platelet-enriched fibrin glue in dogs. Oral Surg Oral Med Oral Pathol Oral Radiol Endod. 2007;103(1):34-37.
37. Khoury F, Keeve PL, Ramanauskaite A, et al. Surgical treatment of peri-implantitis – consensus report of working group 4. Int Dent J. 2019;69 suppl 2(suppl 2):18-22.
38. Froum SJ, Rosen PS. Reentry evaluation following treatment of peri-implantitis with a regenerative approach. Int J Periodontics Restorative Dent. 2014;34(1):47-59.
39. Park SY, Kim KH, Gwak EH, et al. Ex vivo bone morphogenetic protein 2 gene delivery using periodontal ligament stem cells for enhanced re-osseointegration in the regenerative treatment of peri-implantitis. J Biomed Mater Res A. 2015;103(1):38-47.
40. Machtei EE, Kim DM, Karimbux N, Zigdon-Giladi H. The use of endothelial progenitor cells combined with barrier membrane for the reconstruction of peri-implant osseous defects: an animal experimental study. J Clin Periodontol. 2016;43(3):289-297.
41. Daugela P, Cicciù M, Saulacic N. Surgical regenerative treatments for peri-implantitis: meta-analysis of recent findings in a systematic literature review. J Oral Maxillofac Res. 2016;7(3):e15.
42. Ramanauskaite A, Obreja K, Sader R, et al. Surgical treatment of periimplantitis with augmentative techniques. Implant Dent. 2019;28(2):187-209.
43. Aghazadeh A, Persson RG, Renvert S. Impact of bone defect morphology on the outcome of reconstructive treatment of peri-implantitis. Int J Implant Dent. 2020;6(1):33.
Figures and Images
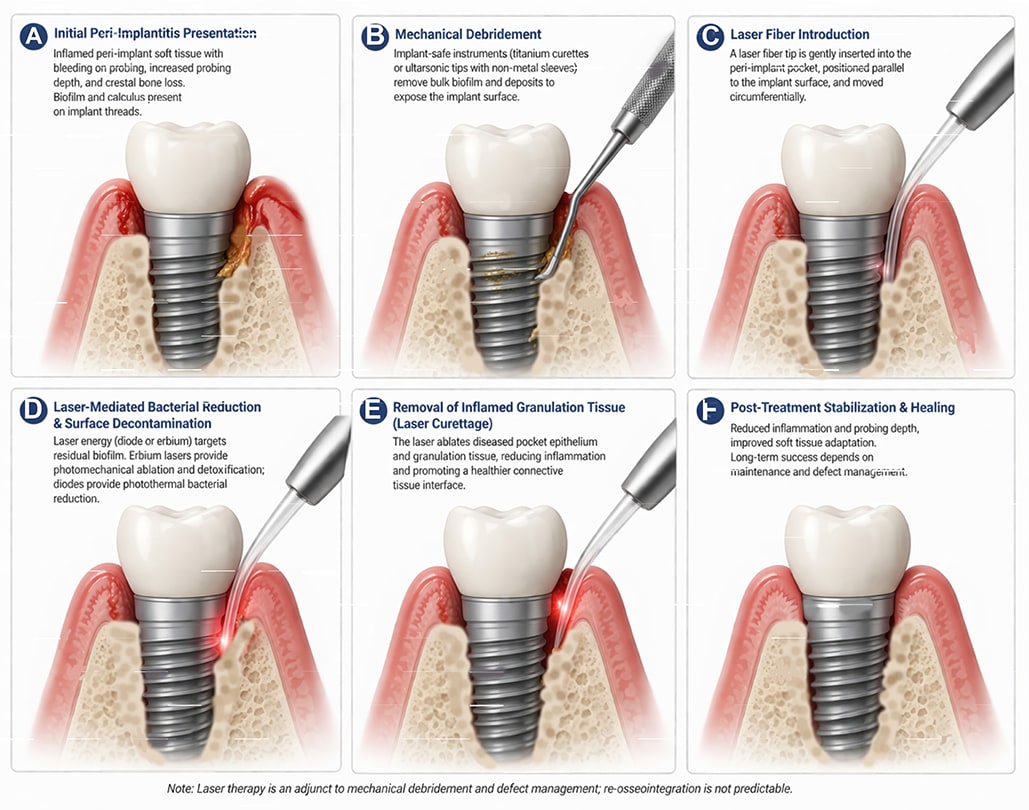
Figure 1
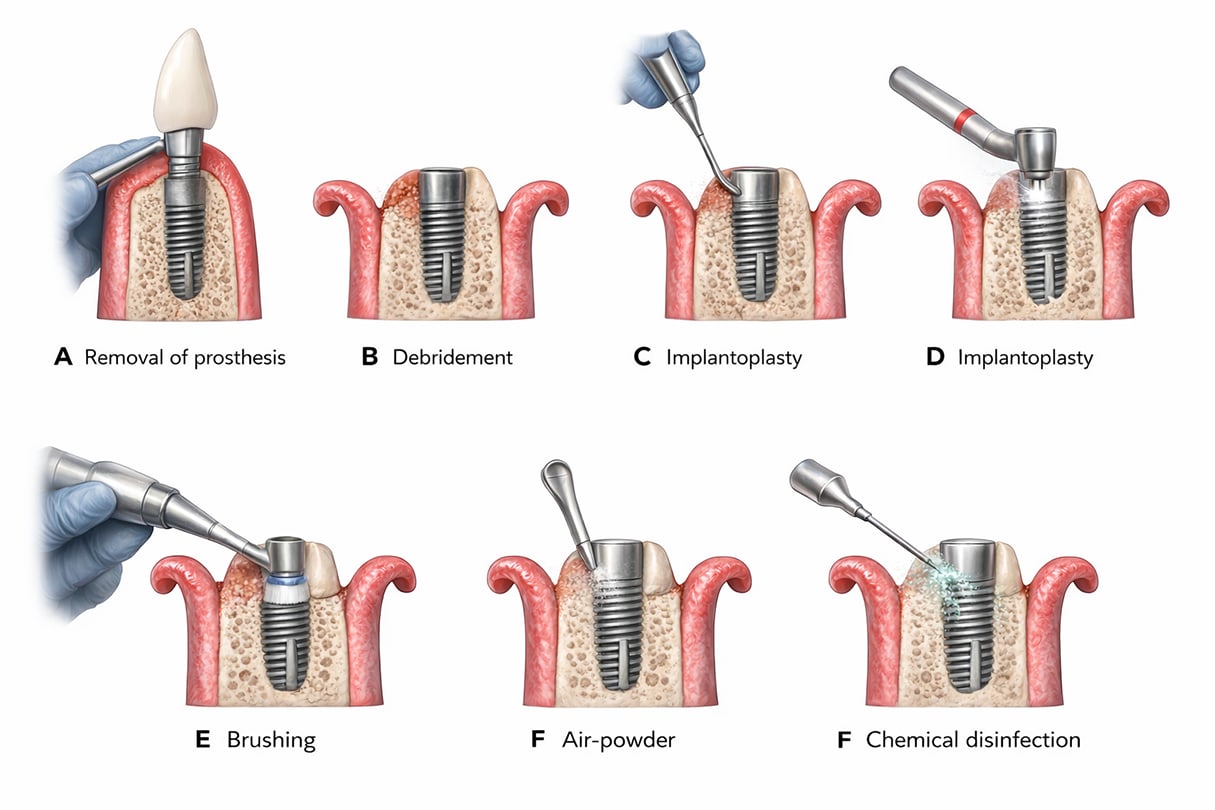
Figure 2
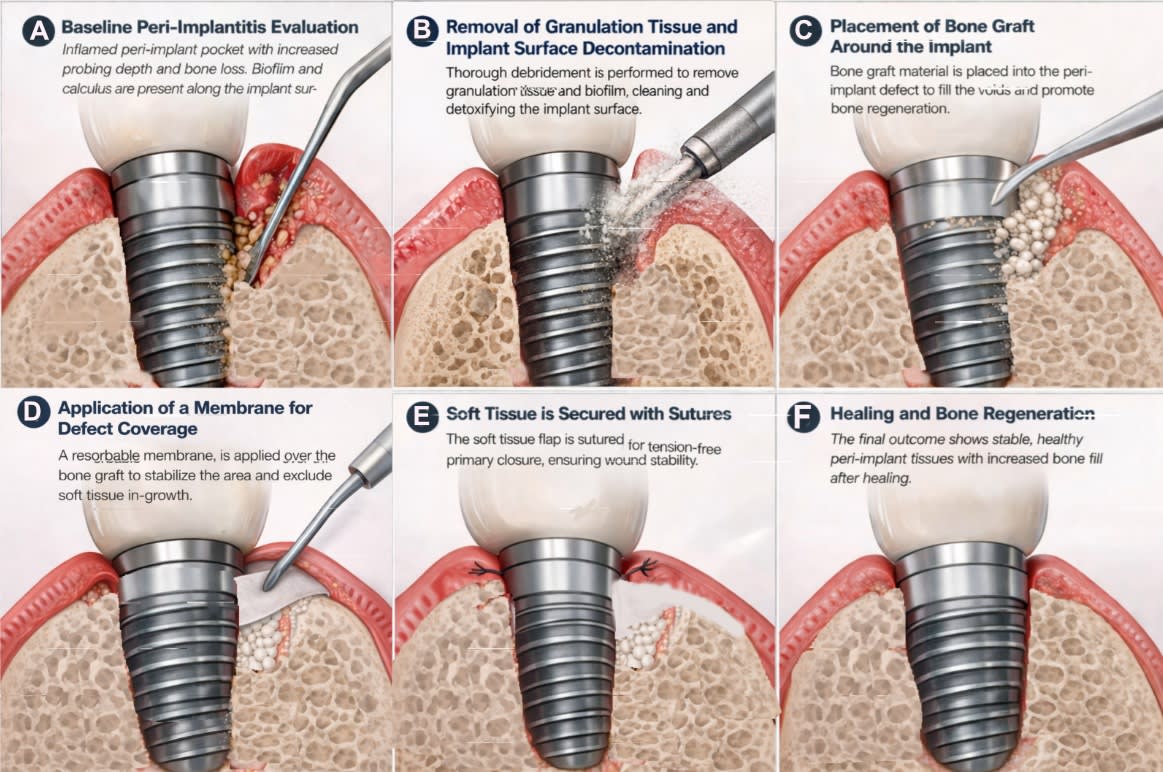
Figure 3
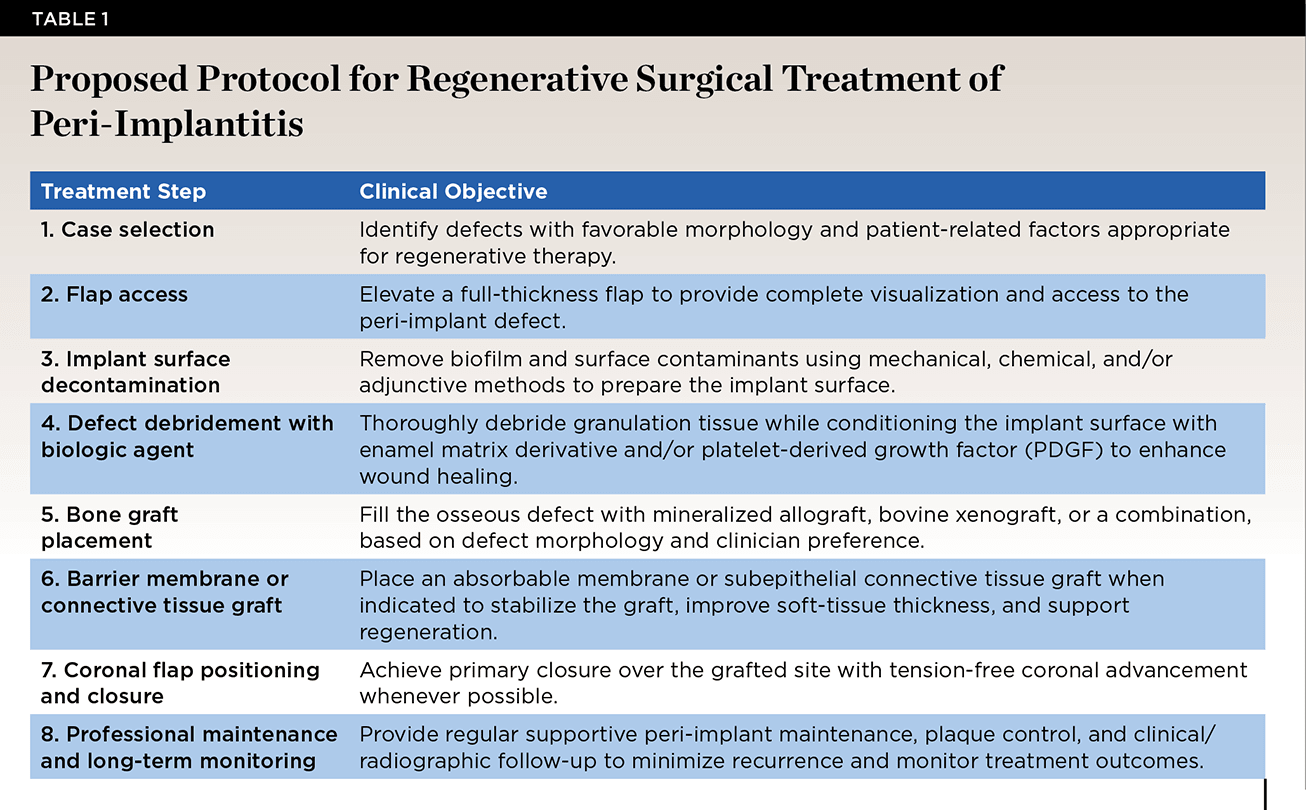
Table 1
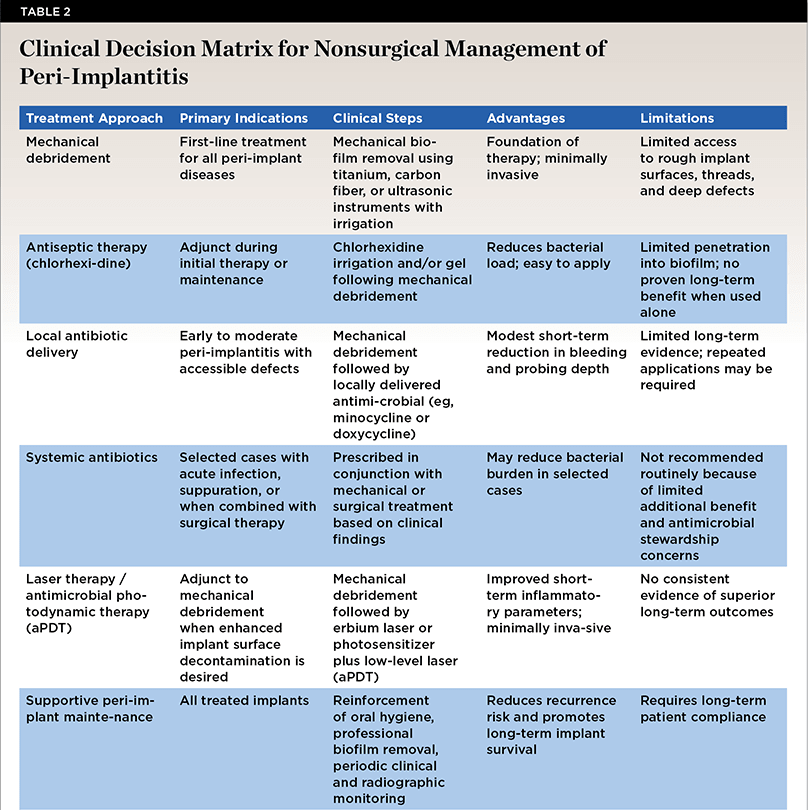
Table 2
